
76 Allds St, Nashua, NH 03060
By Nashua Smile Makers | August 7, 2026
A systematic review examining orthodontic tooth movement in adults found that in patients with stable, treated periodontitis, moving teeth had no significant negative impact on periodontal outcomes. Those findings now inform European Federation of Periodontology guidelines for treating advanced periodontitis.
Active, untreated disease is a different story entirely. Orthodontic force applied to an inflamed, infected periodontium doesn’t just fail to work. It accelerates the damage.
So the question isn’t whether you’ve had gum disease. Roughly 42% of American adults over 30 have some form of it, climbing past 70% after age 65. If a history of gum disease disqualified people from orthodontics, half the adults in Nashua would be out.
The question is whether it’s under control right now.
The Part That Surprises People
Here’s something most patients with gum disease assume backwards.
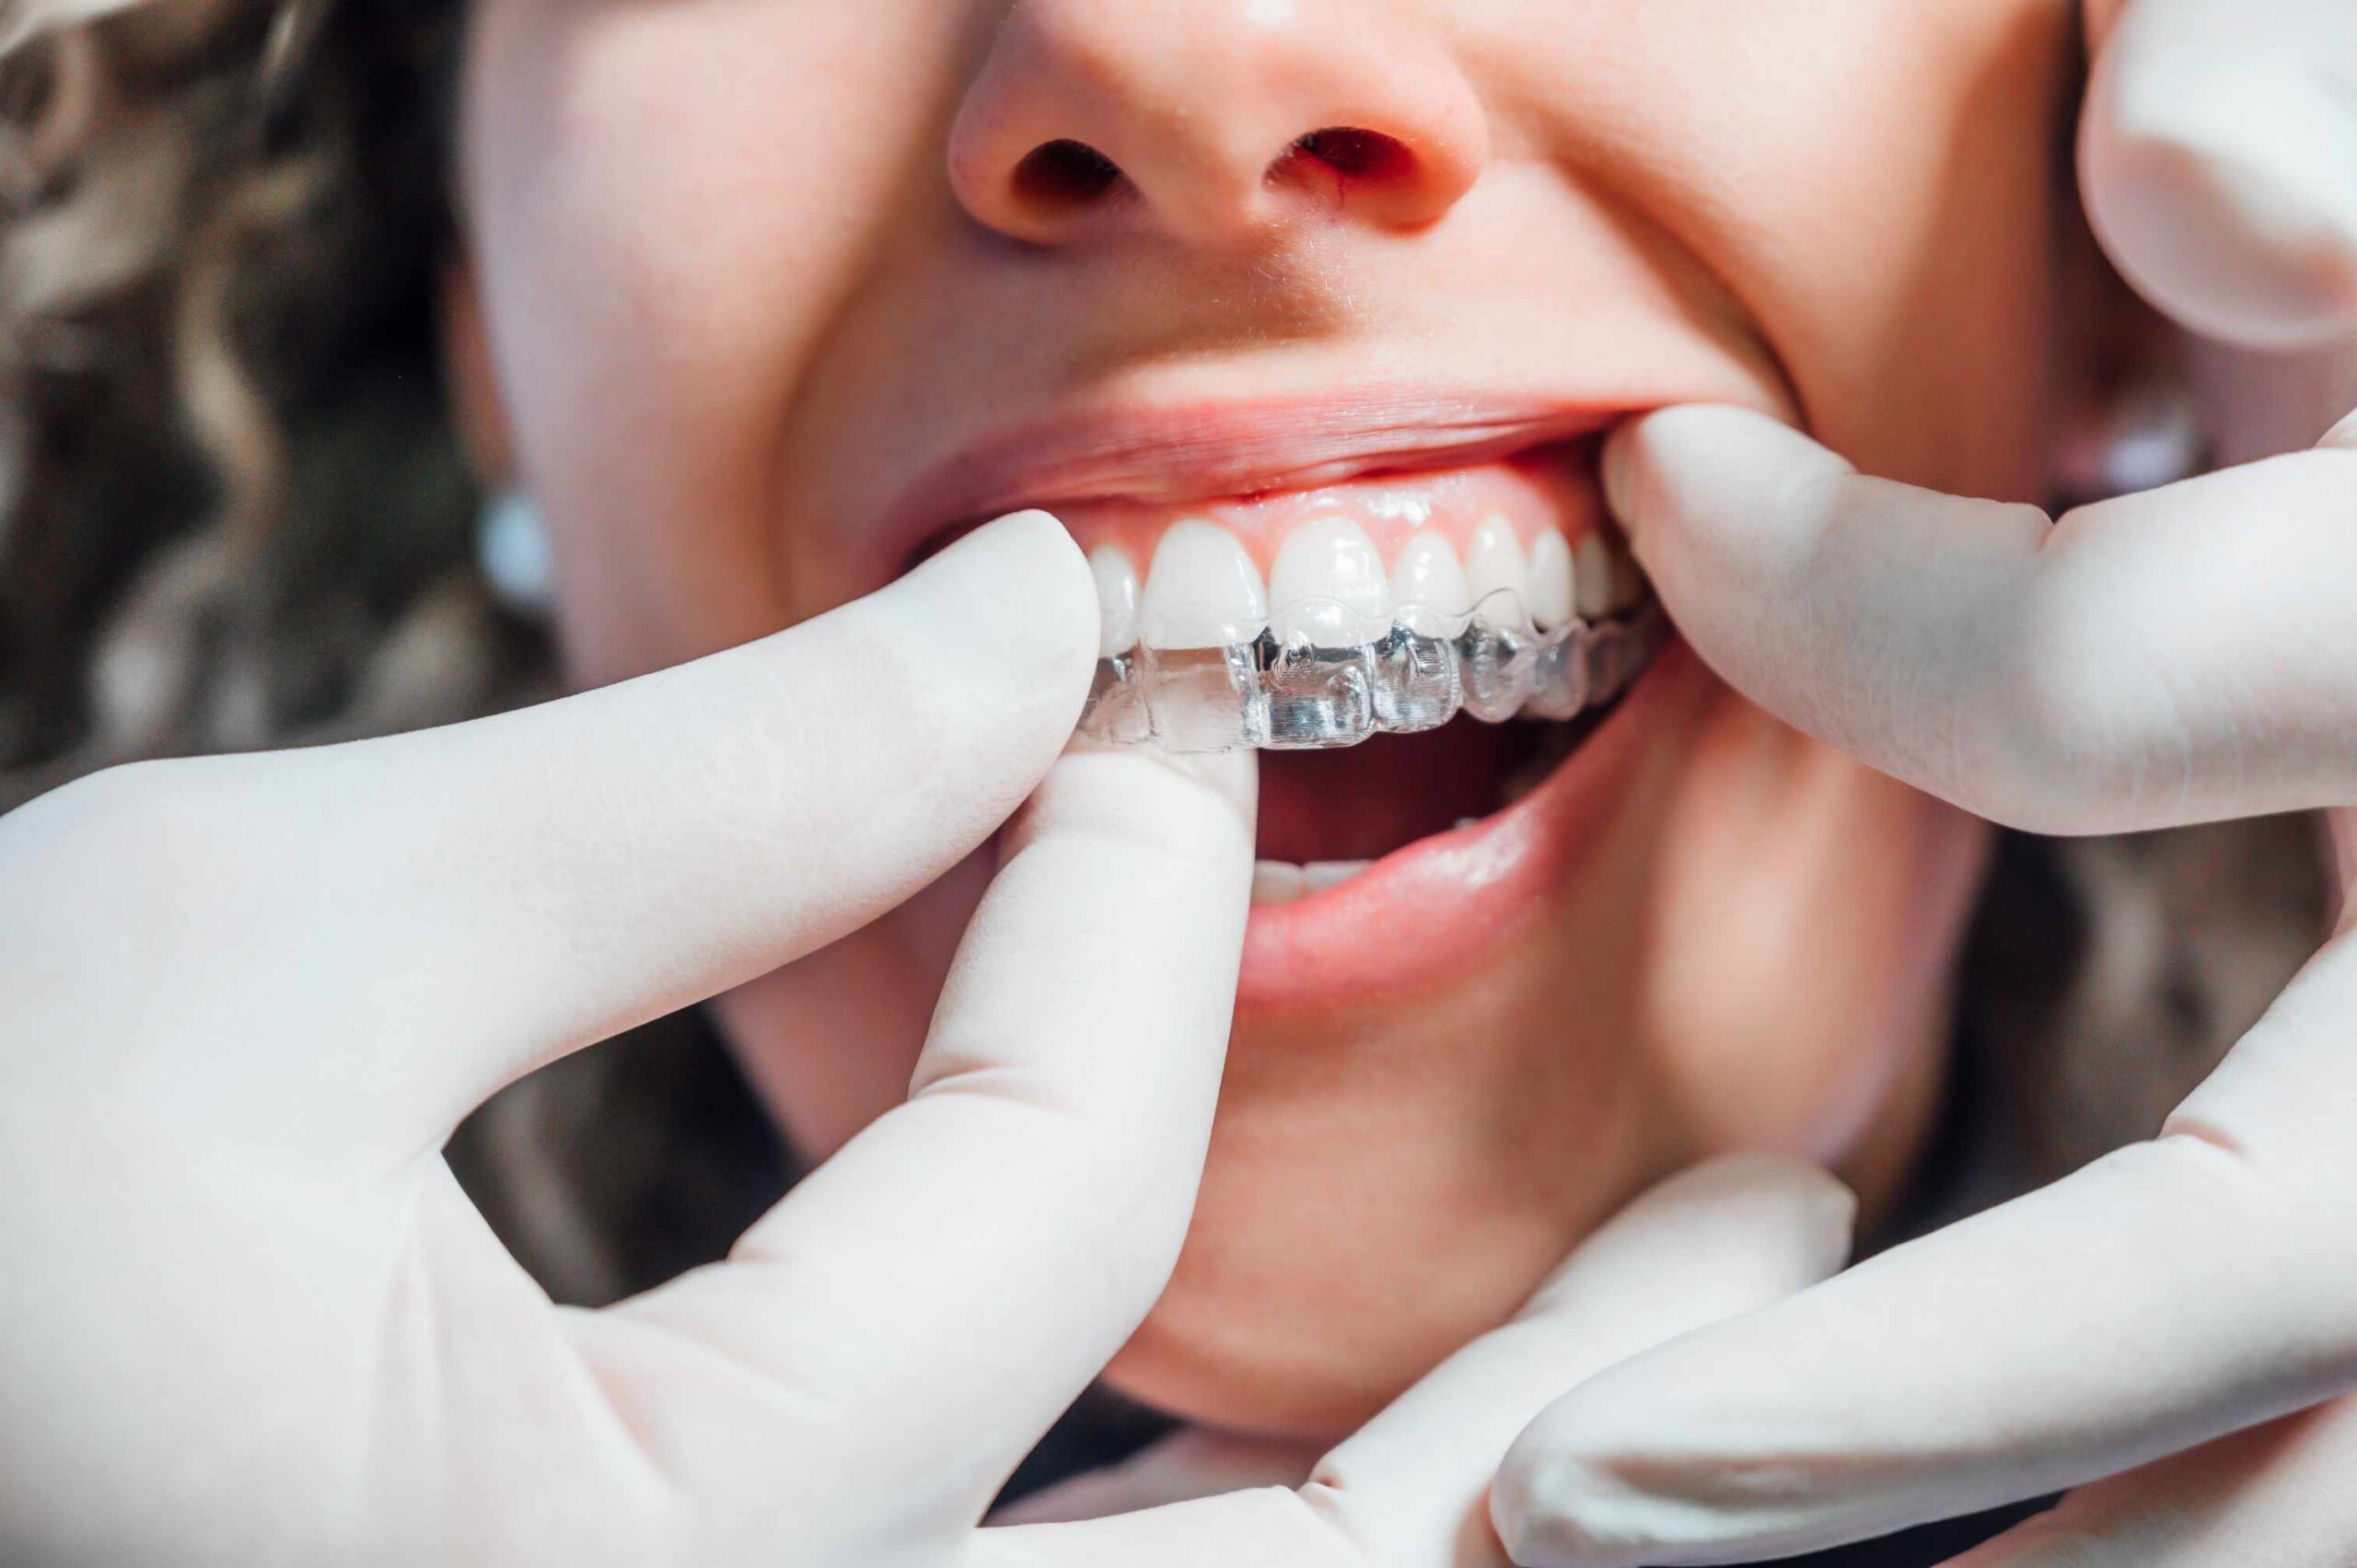
If you have periodontal issues, clear aligners may actually be a better choice for you than traditional braces.
Systematic reviews comparing the two have found that clear aligners improve oral hygiene and reduce inflammation, while fixed appliances can worsen plaque accumulation and periodontal health. Brackets and wires are hard to clean around. Aligners come out.
The evidence extends further than you’d expect. Research on aligner therapy in patients with Stage IV periodontitis, the most advanced category, documented reductions in both pocket depth and attachment loss during treatment. Aligners also apply gentler forces, which matters when bone support is reduced.
So being a periodontal patient doesn’t push you away from Invisalign. In some ways it points toward it.
What Changes When Bone Is Missing
This is the technical part, and it’s worth understanding because it explains why your treatment may look different from your neighbor’s.
When you lose bone around a tooth, the point where force is most effectively applied, what we call the center of resistance, shifts downward toward the root. That reduces our control. Push a tooth the way we would in a patient with full bone support and you risk tipping it rather than moving it bodily, which can cost you more bone.
The response is light, continuous forces and a slower pace. Your treatment may take longer than the estimate a healthy 25-year-old gets, and that’s deliberate.
Some movements also come off the table. Teeth with significantly reduced support can’t be pushed as far or as fast, and part of planning honestly is telling you which goals are realistic.
Expect Black Triangles
I’d rather you hear this now than in month nine.
When teeth are crowded, they overlap and hide the gaps between them. Straighten them and those gaps become visible as dark triangles near the gumline, because the gum tissue can’t fill a space it no longer has the bone to support.
This happens to a lot of adults regardless of gum health. Published figures put black triangle incidence after orthodontic treatment somewhere between 38% and 58% in adults. If you already have bone loss, your odds are higher.
That’s not a complication. It’s physics, and it’s predictable. It’s also treatable afterward with bonding, which is a conversation worth having up front rather than as a surprise.
The Requirement That Doesn’t End
Here’s what separates patients who do well from patients who don’t.
The literature is consistent on this point: an inflammation-free periodontal condition has to be established and maintained throughout orthodontic treatment and beyond. Regular plaque monitoring, hygiene instruction, and professional cleanings are what prevent orthodontic forces from harming an already compromised periodontium.
In practice, that usually means more frequent cleanings during treatment, often every three to four months instead of six. It also means we’re checking pocket depths along the way, not just at the finish.
This is also exactly why mail-order aligner companies are a poor fit for anyone with a periodontal history. No exam, no probing, no radiographs, nobody watching your gums for eighteen months. For a patient with bone loss, that’s not a bargain. That’s a risk.
Why the Same Roof Matters Here
For most dental work, having services under one roof is a convenience. For this, it’s closer to a clinical requirement.
We treat periodontal disease and provide Invisalign in the same practice, which means the same team stabilizes your gums first, watches them during treatment, and adjusts the plan if anything shifts. Nobody hands you off mid-course.
We see this regularly in adults from Nashua, Hudson, Merrimack, Litchfield, Hollis, Amherst, Milford, and Pelham, often people in their forties and fifties who assumed a gum disease diagnosis closed the door on straightening their teeth. Usually it doesn’t. It just changes the order of operations.
Schedule a consultation at our Allds Street office, or meet our dentists first.
Frequently Asked Questions (FAQ’s)
Can you get Invisalign with gum disease?
Yes, once the disease is treated and stable, since research shows tooth movement in stable treated periodontitis has no significant negative periodontal impact.
Can you get Invisalign with bone loss?
Often yes, though reduced bone support requires lighter forces, slower treatment, and sometimes accepting more limited tooth movement.
Is Invisalign better than braces for gum disease patients?
Generally yes, because aligners are removable and allow better cleaning, while fixed braces can increase plaque accumulation and inflammation.
Will Invisalign make my gum recession worse?
Not if your gums are stable and monitored throughout treatment, but active untreated inflammation combined with orthodontic force can accelerate attachment loss.
Do I need gum treatment before starting Invisalign?
Yes, active periodontal disease must be treated and stabilized before orthodontic treatment begins, and maintained throughout.

